
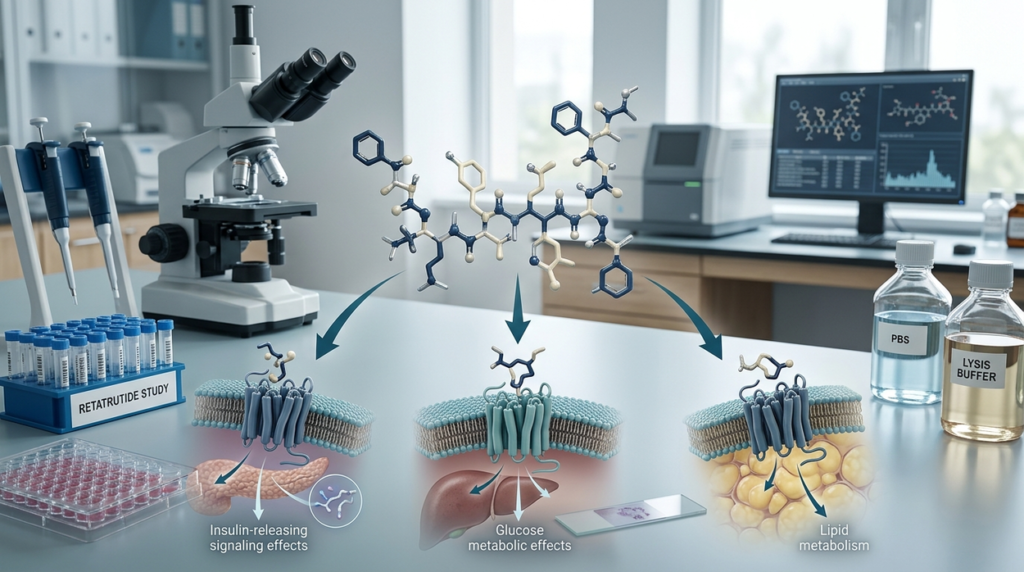
The term “Reta peptide” has become increasingly common in online discussions about obesity and metabolic-drug research. In scientific literature and clinical-trial records, however, the molecule is known as retatrutide, also designated LY3437943. It is an investigational peptide designed to activate three hormone receptors: the GIP receptor, GLP-1 receptor, and glucagon receptor.
That three-receptor mechanism is one reason retatrutide has attracted considerable interest in pharmaceutical research. Rather than targeting GLP-1 signaling alone, retatrutide combines incretin and glucagon pathways in a single molecule. The scientific hypothesis is that these complementary pathways may influence appetite, glucose regulation, energy metabolism and body weight through different but interacting mechanisms.
The clinical evidence has also progressed substantially. A 2023 Phase 2 trial provided an important proof-of-concept, while several Phase 3 studies have subsequently reported positive topline findings during 2025 and 2026. At the same time, an important distinction remains: strong clinical-trial results do not automatically mean that a medicine has been approved or that every reported finding has reached peer-reviewed publication.
This article examines what researchers currently know about retatrutide, what the clinical evidence shows, what remains uncertain, and why the distinction between an investigational medicine and an approved treatment matters.
What Is Reta Peptide? Understanding Retatrutide
“Reta Peptide” vs. Retatrutide
“Reta peptide” is an informal term commonly encountered online. The scientifically recognized name is retatrutide, while LY3437943 is its development code. The U.S. FDA’s substance database also identifies retatrutide as a peptide and lists LY3437943 as a code name.
Using the scientific name is important when researching the molecule because clinical-trial registries, peer-reviewed publications and regulatory documents generally use retatrutide rather than “Reta peptide.”
Retatrutide should also not be treated as simply another name for an approved GLP-1 medicine. It belongs to a broader class of metabolic drugs but has a different pharmacological design.
What Kind of Drug Is Retatrutide?
Retatrutide is a single peptide molecule with agonist activity at three receptors:
- Glucose-dependent insulinotropic polypeptide (GIP) receptor
- Glucagon-like peptide-1 (GLP-1) receptor
- Glucagon receptor
A drug that activates multiple receptors in this way is generally described as a triple agonist or triagonist.
The molecule is being developed as a once-weekly subcutaneous investigational medicine. Lilly’s current development information identifies retatrutide as a large-molecule biologic entity being studied across obesity and several related metabolic or obesity-associated conditions.
How Retatrutide Works at Three Hormone Receptors
The rationale for retatrutide begins with the different physiological functions of its three receptor targets.
GLP-1 Receptor Activity
GLP-1 is an incretin hormone involved in glucose regulation and post-meal physiology. GLP-1 receptor signaling can enhance glucose-dependent insulin secretion and influence appetite and gastrointestinal function.
This pathway has become a major focus of metabolic-drug development. However, retatrutide should not be described as simply equivalent to an approved GLP-1 receptor agonist. Its pharmacology includes two additional receptor targets that change the overall biological profile.
GIP Receptor Activity
GIP, or glucose-dependent insulinotropic polypeptide, is another incretin hormone released in response to nutrient intake. GIP receptor signaling is involved in insulin secretion and broader metabolic regulation.
The development of dual GIP/GLP-1 agonists demonstrated that combining incretin pathways could produce a different pharmacological profile from GLP-1 receptor agonism alone. Retatrutide extends this concept by adding glucagon receptor activity.
Structural and pharmacological research has confirmed that retatrutide can interact with all three receptor systems, providing a molecular basis for its classification as a triple agonist.
Glucagon Receptor Activity
Glucagon has a different physiological role from GLP-1 and GIP. It is involved in maintaining blood-glucose availability and regulating energy metabolism, including effects on hepatic substrate utilization.
That creates an interesting development challenge. Glucagon signaling can increase glucose production, while GLP-1 and GIP signaling can support glucose control and insulin-related effects. Researchers have therefore investigated whether appropriately balanced multi-receptor activity can harness some of glucagon’s metabolic effects without simply reproducing its undesirable effects on blood glucose.
Research reviews describe energy expenditure and substrate metabolism as part of the scientific rationale for incorporating glucagon receptor activity into multi-receptor metabolic medicines.
Why Combine All Three?
The basic hypothesis behind retatrutide is that GIP, GLP-1 and glucagon signaling may complement one another.
In simplified terms:
- GLP-1 signaling contributes to appetite and glucose regulation.
- GIP signaling contributes to nutrient-stimulated insulin secretion and metabolic regulation.
- Glucagon signaling contributes to energy and substrate metabolism.
The important scientific distinction is that a plausible mechanism does not, by itself, prove clinical superiority. Receptor pharmacology provides a rationale for testing the molecule; randomized clinical trials are required to determine whether that rationale translates into meaningful benefits and an acceptable safety profile.
What the Early Clinical Research Found
Phase 1 Research
Early clinical development of retatrutide focused on pharmacokinetics, pharmacodynamics, dose escalation and tolerability. These studies are particularly important for a multi-receptor molecule because investigators must determine how exposure changes with dose and how adverse effects behave as doses are increased.
The findings supported progression into larger controlled trials, where efficacy could be evaluated alongside safety.
The 2023 Phase 2 Obesity Trial
The most important early clinical milestone came from a randomized, double-blind, placebo-controlled Phase 2 trial published in the New England Journal of Medicine.
The study included 338 adults with obesity or overweight plus at least one weight-related condition. Participants received once-weekly subcutaneous retatrutide at different doses or placebo for 48 weeks.
At 48 weeks, the least-squares mean change in body weight was:
| Treatment | Mean percentage change in body weight at 48 weeks |
| 1 mg retatrutide | −8.7% |
| 4 mg, combined groups | −17.1% |
| 8 mg, combined groups | −22.8% |
| 12 mg | −24.2% |
| Placebo | −2.1% |
The 12-mg group therefore showed a 24.2% least-squares mean reduction in body weight at 48 weeks in that Phase 2 population.
The trial also found dose-related gastrointestinal adverse events. The researchers reported that these events were generally mild to moderate, while a lower starting dose reduced some of the gastrointestinal burden. A dose-dependent increase in heart rate was also observed, peaking around week 24 before declining at later time points.
What the Phase 2 Results Could — and Could Not — Establish
The Phase 2 findings were important because they demonstrated a substantial efficacy signal under controlled conditions. But Phase 2 evidence is not the same as a complete regulatory evidence package.
The trial had a relatively small population and a limited treatment duration compared with the longer-term evidence needed for a chronic metabolic medicine. It also excluded people with diabetes and was not designed to establish long-term cardiovascular or other disease-specific outcomes.
🏢 Verified Pharma Manufacturers Directory
Looking for verified and trusted pharmaceutical research partners related to this topic? Explore our comprehensive directory.
Explore Directory →Consequently, the results justified further development rather than providing a basis for assuming that the same results would apply to every population.
That is the purpose of Phase 3: to evaluate efficacy and safety in larger and more clinically diverse populations, using predefined endpoints that can support regulatory decisions.
What Current Phase 3 Research Shows
By September 2026, retatrutide’s development program has moved well beyond the original Phase 2 obesity trial. Several Phase 3 studies have reported results, although the publication status differs between trials.
TRIUMPH-1 and Obesity Without Diabetes
In May 2026, Lilly reported topline results from TRIUMPH-1, a Phase 3 study involving adults with obesity or overweight plus at least one weight-related comorbidity and without diabetes.
At 80 weeks, Lilly reported an average body-weight reduction of 28.3% with the 12-mg dose, compared with 2.2% with placebo. The company also reported 25.9% average weight reduction with 9 mg and 19.0% with 4 mg.
These figures represent company-reported topline results rather than the same level of peer-reviewed evidence available for the 2023 Phase 2 trial. That distinction matters when interpreting the evidence.
Lilly also reported that a subset of participants with baseline BMI of at least 35 who entered an extension continued to lose weight through 104 weeks, with an average reduction of up to 30.3%.
The results are therefore important signals about longer-duration efficacy, but they should not be interpreted as an outcome guaranteed for individual patients.
TRIUMPH-2 in Obesity and Type 2 Diabetes
TRIUMPH-2 examined retatrutide in adults with obesity or overweight and type 2 diabetes.
According to Lilly’s July 2026 topline announcement, participants receiving 4 mg, 9 mg and 12 mg experienced average weight reductions of 12.7%, 19.1% and 20.8%, respectively, at 80 weeks. The corresponding average A1C reductions were 1.4, 1.6 and 1.5 percentage points. The placebo group had a 4.0% average weight reduction and a 0.2-point A1C reduction.
This study is particularly relevant because obesity and type 2 diabetes frequently coexist, while weight-management responses and glycemic outcomes can differ from those observed in people without diabetes.
The results should nevertheless be interpreted within the specific characteristics of the trial population. They do not automatically establish how every person with type 2 diabetes would respond.
TRIUMPH-3 and Cardiovascular Disease
TRIUMPH-3 studied adults with severe obesity and established cardiovascular disease, with or without type 2 diabetes.
Lilly reported average weight reductions of 21.6% at 9 mg and 22.6% at 12 mg at 80 weeks, compared with a 3.2% reduction with placebo.
The study also provides an important example of why weight-loss results and cardiovascular outcomes should not be conflated.
In a prespecified analysis, Lilly reported 44 MACE-5 events in the pooled retatrutide groups and 52 in the placebo group, producing a hazard ratio of 0.82 with a 95% confidence interval of 0.55 to 1.22. For MACE-3, the reported hazard ratio was 1.12 with a 95% confidence interval of 0.64 to 1.96.
These estimates have wide confidence intervals and do not establish a cardiovascular-event reduction. A cardiovascular outcomes program therefore remains important for determining the longer-term clinical implications.
TRANSCEND-T2D-1 and Type 2 Diabetes
Retatrutide has also generated peer-reviewed Phase 3 evidence in type 2 diabetes.
The TRANSCEND-T2D-1 trial was a 40-week, randomized, double-blind, placebo-controlled Phase 3 study involving adults whose type 2 diabetes was inadequately controlled with diet and exercise alone. It was conducted at 48 sites in the United States, Mexico and India.
The study was published in The Lancet in June 2026, providing an important example of how later-stage retatrutide evidence is beginning to move from company announcements into peer-reviewed literature.
TRIUMPH-4 and Other Investigational Areas
The development program has also expanded into obesity-associated conditions.
In TRIUMPH-4, Lilly reported 68-week results in adults with obesity or overweight and knee osteoarthritis without diabetes. The company reported average body-weight reductions of 26.4% with 9 mg and 28.7% with 12 mg, together with improvements in knee osteoarthritis pain measures.
Other areas under investigation include obstructive sleep apnea, chronic low back pain, cardiovascular and renal outcomes, and metabolic dysfunction-associated steatotic liver disease (MASLD). Lilly’s current development information lists these among the areas being evaluated.
These programs are significant because they move the research question beyond weight reduction alone. Researchers are increasingly interested in whether metabolic medicines can affect the clinical complications associated with obesity.
What the Research Says About Weight Loss — and What It Does Not Say
Understanding Percentage Weight Loss in Clinical Trials
A reported 20% or 28% reduction in body weight is a group-level clinical-trial result, not a prediction for an individual.
Percentage weight change is calculated relative to baseline body weight. Researchers then compare changes between treatment groups using statistical methods designed around the trial’s predefined estimands.
Individual responses can vary substantially because participants differ in baseline characteristics, adherence, biological response, concomitant treatment and other factors.
Therefore, a statement such as “retatrutide produces 28% weight loss” is less precise than saying that a particular Phase 3 study reported a specified average treatment-group reduction at a defined dose and time point.
Why Dose and Treatment Duration Matter
Retatrutide trials have used dose-escalation strategies because tolerability can influence how participants remain on treatment.
The Phase 2 study showed that gastrointestinal adverse events were dose-related and that a lower starting dose could reduce some tolerability problems.
Duration also matters. A 48-week study and an 80-week study do not answer exactly the same question. Longer follow-up can reveal whether weight reduction continues, plateaus, or changes over time.
Why Cross-Trial Comparisons Can Be Misleading
Online discussions often compare retatrutide directly with semaglutide or tirzepatide.
Such comparisons require caution unless the medicines have been evaluated in appropriately designed head-to-head trials. Differences in study populations, baseline BMI, treatment duration, dose, dose-escalation schedules, endpoints and statistical estimands can materially affect the reported result.
A number from one clinical trial should therefore not automatically be compared with a number from a different trial and interpreted as evidence that one drug is superior.
Safety and Tolerability Remain Central to Retatrutide Research
Gastrointestinal Adverse Events
Gastrointestinal adverse events were among the most common events reported in the Phase 2 trial. These included effects characteristic of the broader incretin-based drug class, and the frequency increased with dose.
This makes dose escalation an important component of clinical development rather than simply a technical dosing detail.
🏢 Verified Pharma Manufacturers Directory
Looking for verified and trusted pharmaceutical research partners related to this topic? Explore our comprehensive directory.
Explore Directory →Heart Rate and Other Physiological Signals
The Phase 2 trial observed dose-dependent increases in heart rate, with the increase peaking around week 24 and declining afterward.
For a multi-receptor metabolic medicine, such physiological signals warrant continued investigation because the ultimate risk-benefit assessment depends on both short-term tolerability and longer-term clinical outcomes.
What Longer-Term Safety Studies Need to Establish
Important questions include:
- How safety changes with prolonged exposure
- Whether rare adverse events emerge in larger populations
- How cardiovascular outcomes compare over time
- Whether safety profiles differ between populations with and without diabetes
- How renal and hepatic outcomes develop
- Whether benefits and adverse effects persist during extended treatment
A large Phase 3 program can provide more information than Phase 2, but the evidence base continues to mature as additional participants and longer follow-up become available.
Why Topline Results Are Not the Same as a Complete Safety Evidence Base
A company press release can provide important information about a clinical-trial milestone, but a topline announcement typically contains less methodological and subgroup detail than a full peer-reviewed publication.
Peer-reviewed reports allow readers to examine study design, statistical methods, participant disposition, adverse events and predefined endpoints in greater detail.
For this reason, 2026 Phase 3 announcements should be described accurately as company-reported topline results until the corresponding detailed publications are available.
Is Retatrutide Approved or Available for Public Use?
As of September 2026, retatrutide is not approved by the FDA or any other regulatory agency, according to Lilly’s current information. It remains an investigational medicine being evaluated in clinical trials.
The FDA has separately stated that retatrutide is not an FDA-approved component and cannot be used in compounding under federal law.
This is an important distinction because successful Phase 3 trials and regulatory approval are separate milestones.
Why “Successful Phase 3” Does Not Mean “Approved”
Phase 3 studies generate evidence that can support a regulatory submission. The regulator must then evaluate the submitted evidence, including matters such as:
- efficacy
- safety
- benefit-risk balance
- manufacturing quality
- product consistency
- proposed indication
- labeling and other regulatory requirements
A positive Phase 3 announcement therefore means that a sponsor has reported favorable trial findings against specified endpoints. It does not mean that a regulator has already authorized the medicine.
The Planned Regulatory Submission
Lilly reported in July 2026 that it planned to submit a Biologics License Application (BLA) to the FDA in the first quarter of 2027.
That is a company-reported development plan, not an FDA decision or approval date. The regulatory position should therefore be checked again whenever this article is updated.
For current regulatory terminology and official approval information, the FDA’s drug-information resources provide the appropriate reference point. FDA drug information and regulatory resources
Why Unapproved “Reta Peptide” Products Require Extra Caution
The popularity of the term “Reta peptide” has created an important distinction between clinical-trial retatrutide and products marketed online as retatrutide.
An investigational medicine used in a regulated clinical trial is manufactured, handled and administered under a defined development protocol. A product sold through an unapproved source does not automatically have the same identity, purity, potency, manufacturing controls or storage history.
Lilly currently states that retatrutide is not available for public use and warns against products claiming to contain retatrutide outside its clinical trials.
The FDA has also specifically warned about unapproved retatrutide products and states that retatrutide cannot be used in compounding under federal law.
For researchers and industry readers, this distinction is especially important because the phrase “research peptide” does not establish that a product is authentic, appropriately manufactured or suitable for human use.
What Researchers Still Need to Learn About Retatrutide
The growing Phase 3 evidence answers some questions while opening others.
Long-Term Efficacy
Researchers still need longer-duration evidence to determine how weight reduction behaves over multiple years.
Key questions include whether weight reduction eventually plateaus, whether the effect remains stable with continued treatment, and what happens after treatment is discontinued.
Long-Term Safety
Large and extended studies are needed to characterize uncommon adverse events and understand safety across broader patient populations.
Cardiovascular and renal outcomes are particularly important areas because obesity and type 2 diabetes themselves are associated with substantial long-term disease risk.
Disease-Specific Outcomes
Retatrutide is being investigated across several conditions rather than obesity alone, including:
- Type 2 diabetes
- Cardiovascular disease
- Knee osteoarthritis associated with obesity
- Obstructive sleep apnea
- Chronic low back pain
- Renal outcomes
- MASLD
Each indication requires its own evidence because improvement in body weight does not automatically prove improvement in a particular disease outcome.
The Next Generation of Metabolic Medicines
Retatrutide is part of a broader movement toward multi-receptor metabolic pharmacology.
Researchers are exploring whether simultaneously modulating different hormonal pathways can produce complementary effects that are difficult to achieve through a single receptor.
That does not mean every multi-receptor approach will succeed. It does demonstrate how drug development is increasingly moving from single-target concepts toward carefully engineered combinations of biological signals.
🏢 Verified Pharma Manufacturers Directory
Looking for verified and trusted pharmaceutical research partners related to this topic? Explore our comprehensive directory.
Explore Directory →How to Read New Retatrutide Research Critically
The rapid pace of retatrutide development makes evidence quality especially important.
Check the Trial Phase and Population
Before interpreting a result, identify:
- Phase 1, Phase 2 or Phase 3
- Number of participants
- Obesity versus overweight population
- Presence or absence of type 2 diabetes
- Cardiovascular disease status
- Other inclusion and exclusion criteria
- Treatment duration
The population is particularly important. A result from adults with obesity without diabetes should not automatically be applied to people with type 2 diabetes or established cardiovascular disease.
ClinicalTrials.gov can provide useful information about study design, eligibility criteria, endpoints and study status. For example, the TRIUMPH-1 registry identifies the study as NCT05929066 and provides details of its design and participant population.
Look Beyond the Headline Number
A reported percentage change in body weight is only one part of a clinical trial.
Readers should also examine:
- Primary endpoint
- Secondary endpoints
- Treatment duration
- Dose and escalation schedule
- Sample size
- Participant completion and discontinuation
- Adverse events
- Statistical confidence intervals
- Missing-data handling
- Prespecified versus exploratory analyses
This becomes particularly important when interpreting press releases that highlight selected topline outcomes.
Distinguish Peer-Reviewed Data From Company Announcements
Not all 2026 retatrutide evidence currently has the same publication status.
The 2023 obesity Phase 2 trial is available as a peer-reviewed New England Journal of Medicine publication. Peer-reviewed Phase 2 retatrutide study in NEJM
The 2026 TRANSCEND-T2D-1 Phase 3 results have also been published in The Lancet.
By contrast, Lilly’s July 2026 announcements for TRIUMPH-2 and TRIUMPH-3 were topline reports, with the company stating that detailed results would be presented at future medical meetings and published in peer-reviewed journals.
That difference does not make a topline result irrelevant. It simply means the level of publicly available methodological detail is different.
Conclusion
Retatrutide, sometimes called “Reta peptide” in informal online discussions, represents a distinct approach to metabolic-drug development. Its scientific identity is much more precise: retatrutide (LY3437943) is an investigational triple agonist of the GIP, GLP-1 and glucagon receptors.
The evidence has progressed considerably since the 2023 Phase 2 obesity trial. That study demonstrated substantial weight reduction over 48 weeks, while Phase 3 programs reported during 2025 and 2026 have extended the investigation into obesity, type 2 diabetes, cardiovascular disease, knee osteoarthritis and other obesity-associated conditions. Some of the newer findings are already peer-reviewed, while others remain company-reported topline results awaiting detailed publication.
Three points are especially important when evaluating the current evidence:
- Retatrutide’s triple-receptor mechanism provides a distinct scientific approach to metabolic disease research.
- Clinical research through 2026 has produced substantial efficacy signals across multiple Phase 3 programs, but individual results must be interpreted within their specific trial populations and designs.
- Long-term safety, broader clinical outcomes, regulatory review and full peer-reviewed publication of newer findings remain important parts of the evidence picture.
For pharmaceutical and biotechnology researchers, the most useful way to follow retatrutide is therefore not through isolated weight-loss headlines, but through the progression of its clinical evidence, safety data, disease-specific outcomes and regulatory review.
FAQs
1. What is Reta peptide?
“Reta peptide” is an informal term commonly used online for retatrutide (LY3437943). Retatrutide is an investigational peptide that activates the GIP, GLP-1 and glucagon receptors.
2. What does retatrutide do?
Retatrutide is designed to produce simultaneous activity at three hormone receptors involved in metabolic regulation. Researchers are studying how this combination affects body weight, glucose control and obesity-related conditions.
3. Is retatrutide approved?
No. As of September 2026, retatrutide remains an investigational medicine and has not been approved by the FDA. Lilly has reported plans to submit a BLA to the FDA in Q1 2027, but that planned submission is not an approval.
4. What does current research show about retatrutide?
The 2023 Phase 2 trial demonstrated substantial weight reduction, while several Phase 3 programs have subsequently reported positive topline findings in obesity and related metabolic conditions. Some Phase 3 evidence has been peer-reviewed, while other recently announced results remain awaiting full publication.
5. Why is retatrutide different from GLP-1 medicines?
Retatrutide is not limited to GLP-1 receptor activity. It is designed as a triple agonist, activating GIP, GLP-1 and glucagon receptors. This multi-receptor mechanism is the central scientific feature being investigated in its clinical-development program.


